What the Anion Gap Measures
The anion gap is a calculated value that helps doctors check for problems in electrolytes and general acid-base balance. It is not a literal measurement of a single substance. Instead of that, it indicates the relationship between major measured ions in the blood, particularly sodium, chloride, and bicarbonate. Because the body preserves a tightly regulated buffer system, changes in this number can point to an underlying metabolic acidosis or another form of electrolyte imbalance.
In plain language, the anion gap can reveal whether there are unmeasured acids in the bloodstream. Those acids can include organic acids produced during illness, poor perfusion, or altered metabolism. A lower or higher value is not a diagnosis by itself, but it can support laboratory interpretation and help identify the cause of a patient’s symptoms or abnormal serum electrolytes.
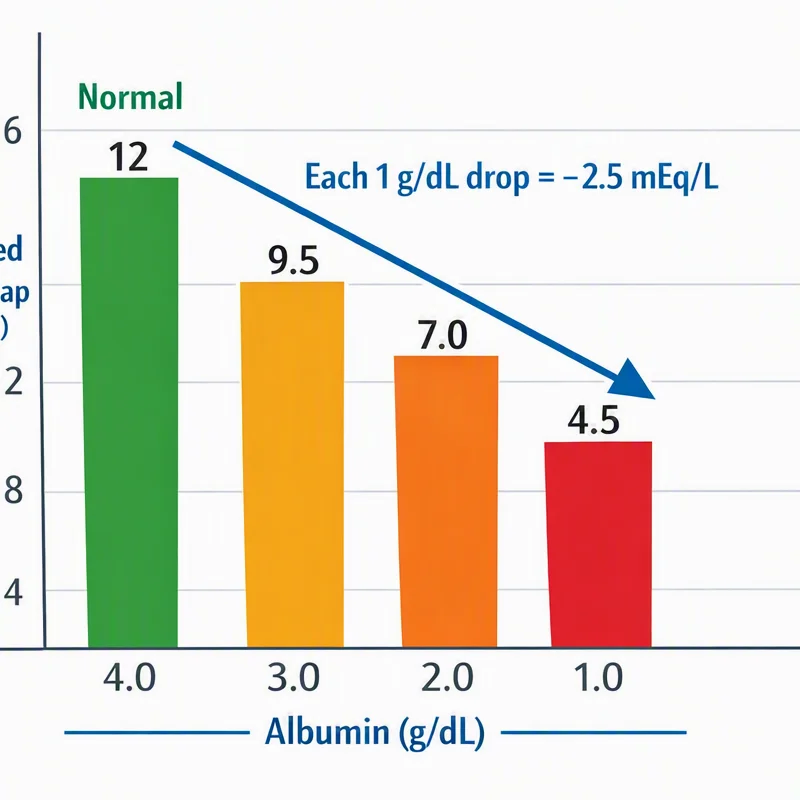
Albumin matters too. Because albumin is a negatively charged protein, it contributes to the usual gap seen on blood testing. If albumin is low, the anion gap may look falsely normal or only mildly elevated even when clinically important acids are present. That is why clinicians often consider albumin correction when reviewing results.
Understanding the anion gap is especially useful because it is part of routine metabolic panel analysis and can reflect changes in renal function, acid production, and clearance. It is one of the most practical ways to think about hidden acid buildup in the blood.
How an Anion Gap Calculator Functions
An Anion Gap Calculator relies on measured lab values to determine the gap quickly. The standard anion gap formula is usually:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some versions also add potassium, but the sodium-based formula is the most commonly used. The calculator is easy to use, but the interpretation is not. A result must always be viewed in clinical context, because the same number can mean different things depending on symptoms, medications, hydration status, and related laboratory findings.
The calculator is helpful because it transforms routine blood chemistry into a more meaningful signal. If sodium stays stable while chloride rises or bicarbonate falls, the calculated gap can decrease or change in a way that suggests altered acid handling. If bicarbonate drops and chloride does not fully compensate, the gap may rise, creating an elevated anion gap or high anion gap result.
Many people use the calculator as a quick tool for understanding a metabolic panel. But it should never be treated as a standalone diagnosis tool. The number is only one piece of the full evaluation, and it is most meaningful when paired with other serum electrolytes, glucose testing, and kidney-related markers.
A calculator can reveal the number, but only the full lab picture clarifies why the number changed.
Can Fasting Raise the Anion Gap?
Yes, fasting can in some cases raise the anion gap, especially if it results in ketosis. When the body does not obtain enough carbohydrate from food, it changes its fuel use toward fat. This creates ketone bodies, which are acidic. As ketone production increases, those acids can enter the bloodstream and cause a slight rise in the anion gap.
This pattern is often called starvation ketosis when it happens from reduced intake rather than diabetes. In many healthy people, the effect is limited and temporary. The kidneys and respiratory system usually help maintain acid-base balance, so the result may be a slight, sometimes compensated acidosis rather than severe illness.
That said, fasting does not affect everyone the same way. The size of the change depends on how long the fast lasts, how much carbohydrate anion gap is usually eaten, overall nutrition, blood glucose levels, and whether there are other medical problems. A brief fast for a lab test is much less likely to cause major shifts than prolonged fasting or severe calorie restriction.
In most cases, fasting-related ketosis causes only a modest acid load. But when ketone production becomes substantial, the body may develop a clearer metabolic derangement with an increasing gap. This is why an abnormal result should be interpreted alongside symptoms and related labs, not in isolation.
When Going without food Is More Apt to Change Results
Certain situations make fasting more likely to affect the anion gap. Dehydration is one of the biggest. When fluid intake is low, blood becomes more concentrated, and renal clearance of acids may be less adequate. That can intensify the effect of ketosis or make abnormal values easier to detect.
Low carbohydrate intake also plays a role. If someone is already following a very low-carb approach and then fasts, the body may move more quickly into ketone production. This can increase the amount of ketone bodies circulating in the blood, especially if the fast lasts long enough for stored glucose to become limited.
Prolonged fasting is more likely than short fasting to alter anion gap calculation anion-gap-calculation.com laboratory values. As fasting continues, the body shifts more deeply into fat metabolism and glucose conservation. That change in glucose metabolism can promote ketone production and, in some people, a measurable rise in the anion gap.
Blood glucose level is also important. If glucose is normal or low during fasting, the situation is usually more consistent with nutritional ketosis. If glucose is high, especially in a person with diabetes, the pattern may be much more concerning and could point toward a serious acid-base disorder.
Other factors can interact with fasting too. Vomiting, poor oral intake, infection, and certain medications may all affect hydration status and metabolic stability. The lab picture is often shaped by a combination of factors rather than fasting alone.
Other Frequent Causes of a High Anion Gap
Fasting-related changes are only one potential explanation for a high anion gap. A number of other conditions can cause a comparable pattern and should consistently be considered during laboratory interpretation.
Lactic acidosis happens when the body produces or clears too much lactic acid. This can occur with reduced oxygen delivery, major infection, intense physiologic stress, or some medications. It is an important cause of elevated acids in the blood and can significantly change the anion gap.
Kidney disease can also raise the gap. When the kidneys cannot remove acids effectively, the body holds onto unmeasured acid compounds, increasing the gap and disrupting acid-base balance. In this setting, renal function is a central part of the workup.
Diabetic ketoacidosis is a serious medical emergency in which insulin deficiency leads to severe ketone production and major metabolic acidosis. Although it shares a ketone-related mechanism with fasting ketosis, it is considerably more dangerous and usually causes a far larger laboratory abnormality.
Toxic alcohols such as methanol or ethylene glycol can also cause a high gap because their metabolism generates harmful acidic byproducts. These cases require immediate medical evaluation and are not related to ordinary fasting.
Additional sources of elevated anion gap include certain poisonings and severe systemic illness, but the conditions above are among the most common and clinically important. This is why the gap should always be interpreted with the whole picture in mind, not as a standalone finding.
Signs That Need Medical Attention
Most minor fasting-related shifts rarely cause serious symptoms, but specific warning signs must not be overlooked. When abnormal lab results come with nausea, vomiting, confusion, or shortness of breath, prompt medical attention is important.
These symptoms may reflect worsening metabolic acidosis, marked dehydration, infection, or a different serious condition. Shortness of breath can reflect the body attempting to compensate for acid buildup by altering breathing patterns. Confusion can suggest that the metabolic disturbance is affecting brain function or that another serious issue is present.
Because fasting can overlap with illness, a symptom review matters as much as the numbers. If the person has diabetes, kidney problems, or repeated vomiting, a high anion gap needs prompt evaluation. A single result should not be used to dismiss concerning symptoms.
If there is severe weakness, inability to keep fluids down, chest discomfort, or worsening mental status, immediate assessment may be needed. The purpose of the anion gap is to detect problems early, not to delay care when symptoms point to a more serious issue.
How to Understand Values Together With a Clinician
Interpreting the anion gap correctly requires more than comparing the result to a reference range. Various laboratories use slightly different methods, and the expected range can vary depending on the analyzer and whether potassium is included. That is why the same result may be interpreted differently across clinical environments.
Clinicians often look at the anion gap together with albumin correction. If albumin is low, the corrected value may reveal a hidden elevated gap that would otherwise appear less impressive. This step is especially important when evaluating possible metabolic acidosis in people with long-term illness, inflammatory conditions, liver disease, or poor nutrition.
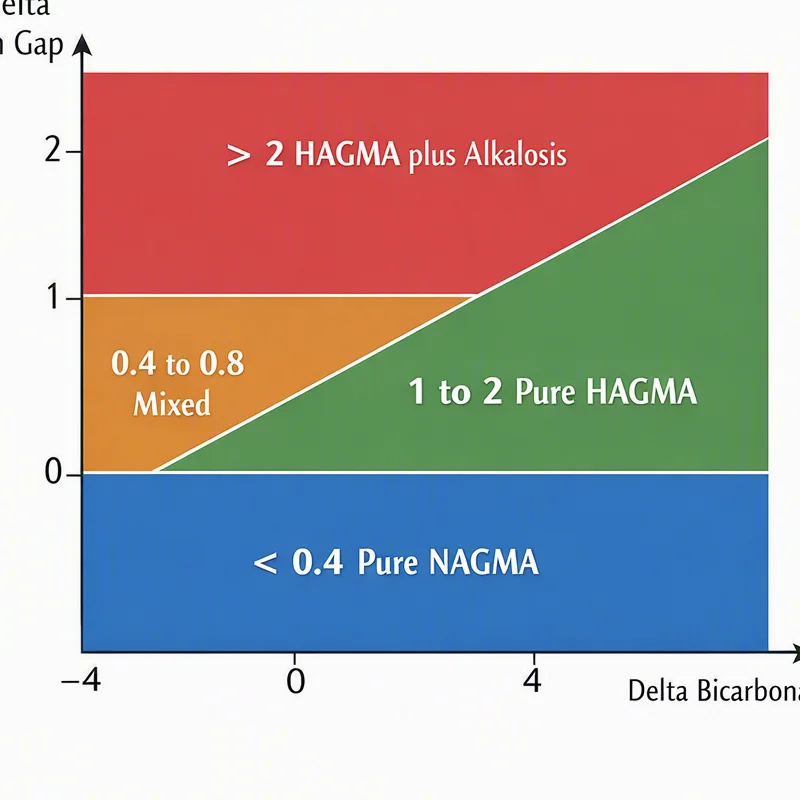
The result should also be placed into the larger picture of acid-base balance. A person can have a high gap with partial respiratory compensation, a normal gap with bicarbonate loss, or a mixed disorder. Understanding these patterns often requires the full comprehensive metabolic panel along with other tests and the clinical story.
An Anion Gap Calculator can be a useful starting point, but it cannot determine the cause on its own. The question is not only whether the number is high, but why it is high, how high it is, and whether the rest of the lab assessment fits with fasting, ketosis, dehydration, kidney disease, or another process.
In practice, clinicians may also consider the patient’s hydration status, glucose metabolism, and recent diet. A modest shift after fasting may reflect a benign, temporary change. A larger or persistent elevation deserves more investigation, especially if there are symptoms or an abnormal comprehensive metabolic panel.
FAQ About Fasting and the Anion Gap
Can fasting cause a high anion gap?
Yes. Fasting can cause a high anion gap if it leads to ketosis and ketone body buildup. This usually happens when the body shifts toward fat breakdown and produces more acidic byproducts. In many people, the rise is mild, but it should still be interpreted in clinical context.
How extended does fasting need to continue to influence the anion gap?
Its impact depends on fasting length, recent food intake, hydration status, and overall condition. A brief fast may have minimal impact, while prolonged fasting is more likely to boost ketone production and alter lab values. There is no universal threshold that applies to everyone.
Is a small rise in anion gap during fasting dangerous?
Not inherently. A small rise can occur with ketone buildup and may not be dangerous if the person feels well and other labs are favorable. However, a worsening gap with symptoms, low bicarbonate, or abnormal blood glucose should be reviewed by a clinician.
What is the difference between fasting ketosis and diabetic ketoacidosis?
Ketosis from fasting usually occurs from limited carbohydrate intake and tends to be less intense. Diabetic ketoacidosis happens when there is not enough insulin, leading to significant ketone production, dehydration, and serious metabolic acidosis. Diabetic ketoacidosis is an emergency and is not the same as ordinary fasting ketosis.
Should I stop fasting if my anion gap is abnormal?
It hinges on the cause and your symptoms. If the abnormal result is slight and you feel well, a clinician may simply want repeat labs or additional context. If you have nausea, vomiting, confusion, shortness of breath, high blood glucose, or a markedly elevated gap, you should seek medical evaluation right away rather than continue fasting.